Rotator cuff repair is surgery that reattaches a torn shoulder tendon to the upper end of the arm bone. Surgeons most often do it with small instruments and a camera through tiny cuts. It is considered when pain and weakness continue after rest, therapy, and other non-surgical care. Recovery is gradual and measured in months.
Ross Wodicka performs rotator cuff repair in Fort Lauderdale when it is the right step, and reviews every alternative with you first.
What is rotator cuff repair, and who is it for?
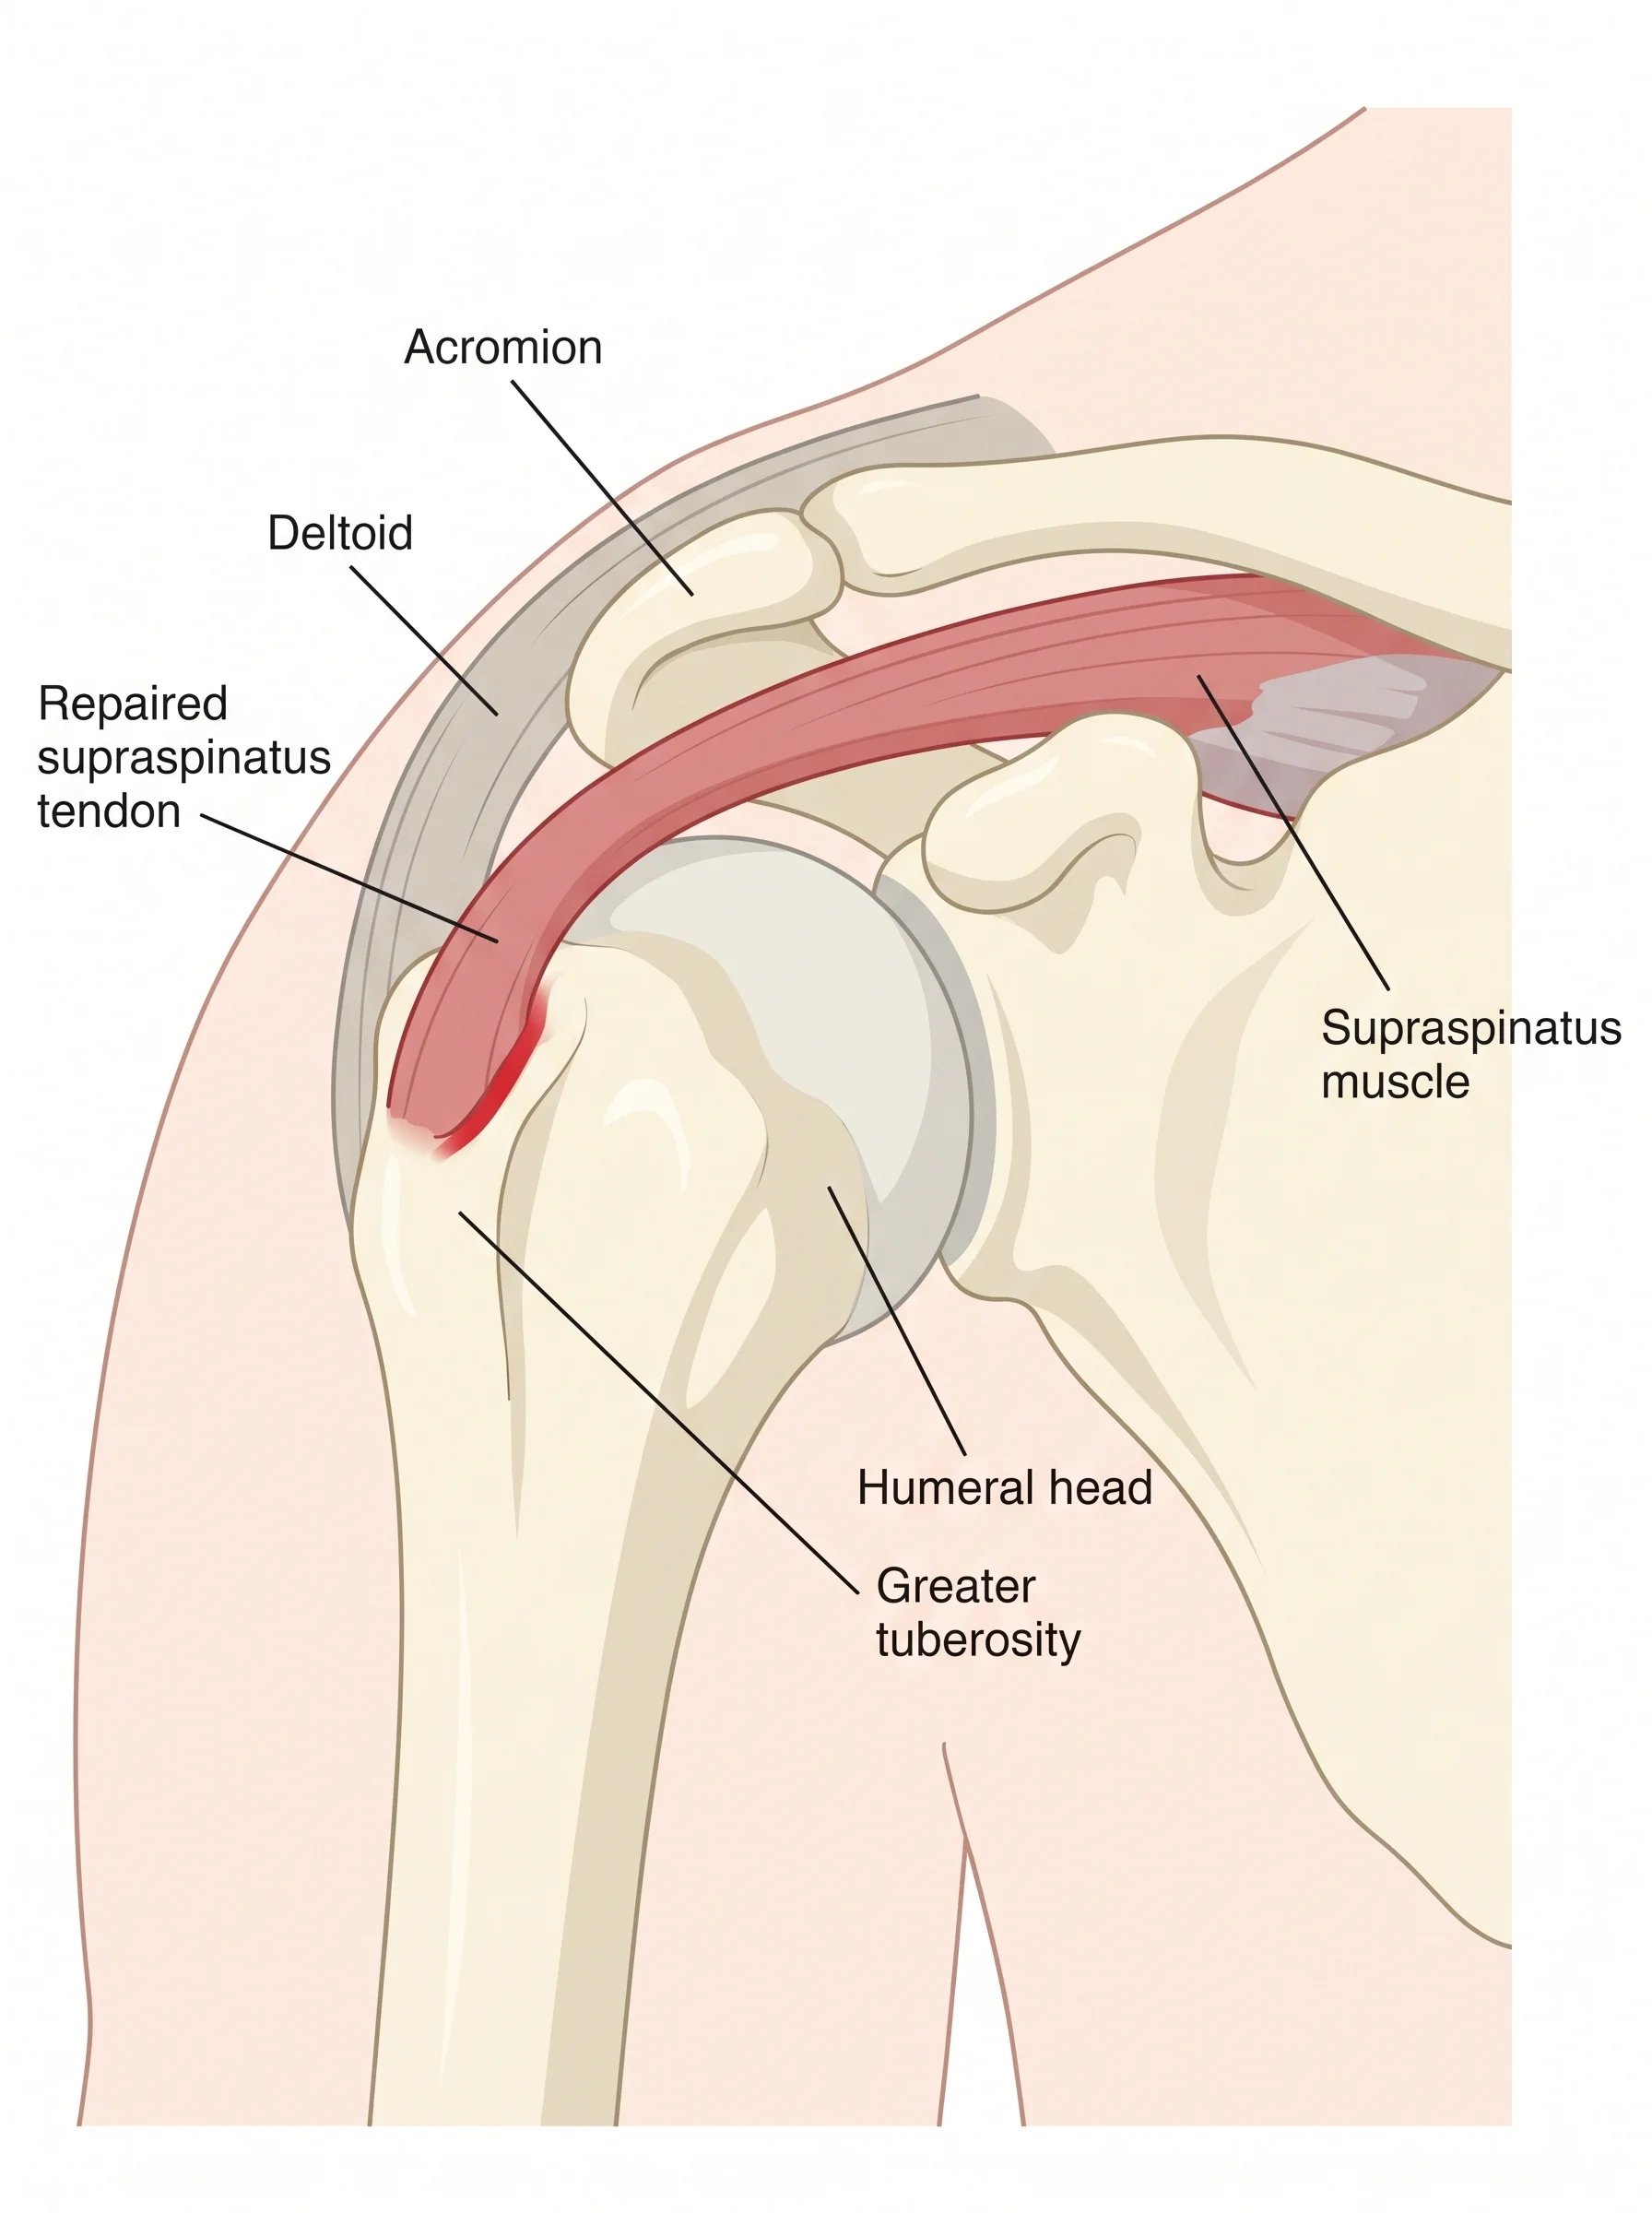
Rotator cuff repair is a procedure that reattaches a torn tendon in the shoulder back to the bone.
The rotator cuff is a group of four muscles and their tendons (the cords that connect muscle to bone) that hold the head of the arm in the shoulder socket and let you lift and rotate the arm. A tear means one of these tendons has pulled partly or fully away from the bone.
Tears happen two ways. Some come on slowly as tendons wear thin with age or repeated overhead use. Others happen suddenly, such as during a fall or a hard lift. Not every tear needs surgery. Many small or partial tears improve with rest, physical therapy, and time. Repair becomes a reasonable conversation when a tear is full-thickness (the tendon is torn all the way through), when weakness limits daily life, or when non-surgical care has not eased pain after a fair trial.
This page explains what a torn cuff feels like, how it is diagnosed, the full range of treatment starting with the non-surgical options, and what surgery and recovery involve if you and your surgeon choose that path.
What do the symptoms feel like, and when should you see a specialist?
The most common signs of a rotator cuff tear are shoulder pain, weakness when lifting the arm, and trouble reaching overhead or behind the back.
Patients often describe it in plain terms.
- A deep ache in the shoulder or upper arm, not usually at the very peak. - Pain that gets worse at night and makes it hard to sleep on that side. - Weakness lifting a gallon of milk, a coffee pot, or a bag of groceries. - Trouble reaching a seatbelt, a back pocket, or a high shelf. - A catching or crackling feeling when moving the arm.
A sudden tear from a fall or lift can cause immediate sharp pain and a quick loss of strength. A slow, wear-related tear may build over months and feel more like a nagging ache.
It is reasonable to see a shoulder specialist if pain lasts more than a few weeks, if weakness is getting worse, or if you cannot lift the arm at all after an injury. Losing the ability to raise the arm after a fall is a reason to be seen sooner. A specialist can tell whether the problem is a tear, tendinitis (irritation of the tendon), bursitis (irritation of the fluid-filled cushion in the joint), or something else. This page describes patterns, it does not diagnose. Only an in-person exam can sort out the cause.
How is a rotator cuff tear diagnosed?
Diagnosis starts with a conversation and a physical exam, then imaging if needed.
At the visit, the surgeon asks how and when the pain started, what makes it better or worse, and how it affects sleep and daily tasks.
During the exam, the surgeon watches how the shoulder moves and gently tests strength in different positions. Specific movements load each of the four cuff tendons, which helps show which tendon is involved and how much strength is lost.
Imaging fills in the picture. X-rays do not show tendons, but they show the bones and can reveal arthritis (joint wear) or bone spurs that add to the problem. Magnetic resonance imaging, called an MRI, uses a magnet and radio waves to make detailed pictures of soft tissue, and it is the main test for seeing a tendon tear, its size, and its quality. Ultrasound, which uses sound waves, is another way to view the tendons and can be done in the office.
The goal of the visit is a clear understanding of the tear and how it fits your life and goals. That picture guides the treatment plan.
[CTA: To have shoulder pain evaluated, request a visit with Dr. Wodicka. Contact and appointment details are on the contact page.]
What happens during Rotator Cuff Repair, step by step?
Rotator cuff repair reattaches the torn tendon to the bone using small anchors and sutures (stitches).
Most repairs today are done with arthroscopy, a technique that uses a pencil-sized camera and thin instruments passed through several small cuts.
Here is the usual sequence:
- Anesthesia. You receive anesthesia so you feel no pain. This is often a nerve block that numbs the arm, combined with sedation or general anesthesia. The anesthesia team reviews the plan with you. - Camera and inspection. The surgeon makes a small cut and inserts the arthroscope, which sends a magnified view to a screen. Saltwater fluid gently expands the joint so structures are easy to see. - Preparing the tendon and bone. The surgeon clears away frayed tissue and prepares the spot on the bone where the tendon will reattach so it can heal. - Placing anchors. Small anchors are set into the bone. These hold strong sutures. - Reattaching the tendon. The sutures are passed through the tendon and tied down, pulling the tendon back against the bone. The surgeon may address related problems in the same setting, such as smoothing a bone spur or trimming inflamed bursa. - Closing. The small cuts are closed and a dressing is applied. Your arm is placed in a sling.
Some tears are repaired through a slightly larger open or mini-open cut, usually when a tear is large or complex. The surgeon chooses the approach that fits your tear. Most rotator cuff repairs are outpatient, meaning you go home the same day.
What is the recovery timeline for Rotator Cuff Repair?
Recovery from rotator cuff repair moves through stages, and the tendon needs time to heal to bone before it is stressed.
The stages below are marked by what you can do, alongside typical ranges. These are ranges, not promises. Your timeline depends on the size of the tear, the quality of the tendon, your health, and your rehabilitation.
Stage 1, protect the repair (roughly the first 4 to 6 weeks). The goal is to let the tendon begin healing. You wear a sling, and the therapist or surgeon may move your arm for you (passive motion) so the joint does not stiffen while you avoid using the muscles yourself. Milestone: you can manage the sling, sleep in a supported position, and do gentle passive motion without sharp pain.
Stage 2, restore motion (roughly 6 to 12 weeks). You gradually begin moving the arm under your own power without added weight. Milestone: you can raise the arm through more of its range and start light daily tasks below shoulder height.
Stage 3, rebuild strength (roughly 3 to 6 months). With the tendon healed to bone, therapy adds resistance to rebuild strength. Milestone: you regain useful strength for lifting and reaching, and you return to most everyday activities.
Stage 4, return to full activity (often 6 to 12 months). Return to heavy lifting, sports, and overhead work is the last step. According to general guidance from the American Academy of Orthopaedic Surgeons, full recovery of strength and motion after rotator cuff repair commonly takes several months to a year, and larger tears take longer. These are ranges, not promises.
Physical therapy is central at every stage. Following the plan, and not rushing it, protects the repair.
Read the full guide to preparing for surgery →
Your own recovery instructions come from the office and are specific to you. This page describes the general course, not a plan to follow.
How should you prepare for surgery?
A little planning before surgery makes the first weeks easier, because you will have one arm in a sling and limited reach on that side.
Use the time before your date to set up.
At home. Place everyday items at waist to chest height so you do not have to reach up or bend low. Stock easy meals and snacks. Set out loose, front-opening shirts, since pullovers are hard with a sling. A recliner or a wedge pillow helps many people sleep more comfortably than lying flat.
Transportation. Arrange for someone to drive you home after surgery and to early appointments. You cannot drive while in the sling or while taking medicine that causes drowsiness, and driving with one working arm is unsafe. Your surgeon will tell you when driving is allowed again.
Time off. Plan time away from work based on your job. Desk work often resumes within a couple of weeks with the arm supported, while jobs that need lifting or overhead reach require much longer. Ask your surgeon for guidance specific to your work.
Help on hand. Have someone available for the first few days to help with meals, dressing, and household tasks. Bathing takes planning, since the incisions stay dry at first.
Health prep. Follow all instructions about which medicines to stop or continue, and about not eating or drinking before surgery. If you use tobacco, know that it slows tendon healing, and any step to cut back before surgery helps.
Which warning signs should you call about?
Most recoveries are smooth, but certain signs need a prompt call to the surgical office.
Call the office if you have.
- Fever, chills, or spreading redness and warmth around the incisions, which can signal infection. - Drainage of pus or a foul smell from an incision. - Pain that suddenly worsens and is not helped by your prescribed medicine. - Numbness, tingling, or fingers that turn pale or blue and do not improve when you change position. - Calf pain, swelling, or new shortness of breath or chest pain.
New shortness of breath, chest pain, or a swollen painful calf can signal a blood clot and is a reason to seek emergency care right away by calling your local emergency number. For questions about the incision, the sling, pain medicine, or activity, call the surgical office. After hours, use the on-call number your team provides. When in doubt, it is always fine to call and ask.
What results can you expect from Rotator Cuff Repair?
Rotator cuff repair relieves pain and improves function for most patients, though healing takes months and results vary.
According to general guidance from the American Academy of Orthopaedic Surgeons, most people who have rotator cuff repair report less pain and better shoulder use after recovery. Success depends on the size of the tear, the quality of the tendon, and how closely rehabilitation is followed. These are general ranges, not promises for any one person.
Larger tears and tears in older tendons carry a higher chance that the tendon does not fully heal to bone, according to general orthopaedic literature summarized by the American Academy of Orthopaedic Surgeons. Even when full healing is not achieved, many patients still report meaningful pain relief. Your surgeon can explain what the size and quality of your tear mean for your likely course. The honest answer is that surgery improves the odds of a strong, comfortable shoulder, and the outcome is shaped by your tear and your effort in therapy.
What do patients ask most?
How long will I wear the sling?+
Will the surgery be arthroscopic?+
Is rotator cuff repair outpatient?+
When can I drive again?+
Does a torn rotator cuff always need surgery?+
How much does it cost?+
What are the treatment options?
- 01Activity changesEasing off overhead work and painful motions gives an irritated tendon a chance to settle.
- 02Physical therapyGuided exercises strengthen the muscles around the shoulder blade and the remaining cuff, which can improve function even when a tear is present.
- 03Anti-inflammatory medicineOver-the-counter or prescribed medicine can lower pain and swelling. A pharmacist or physician can advise on what is safe for you.
- 04Cortisone injectionA steroid shot into the shoulder can reduce inflammation and pain for a period of time and can make therapy easier. It is not a cure and is used thoughtfully.
Fellowship trained at Southern California Orthopedic Institute, Los Angeles (Sports Medicine). Sees patients in Fort Lauderdale.
About Dr. Wodicka →